Emergency pain is not tidy. It shows up in layers, formed by physiology, concern, context, and the clock. I have seen a calm teenager grit teeth via a fractured span, and an older male spiral from a simple hip crack right into delirium because his pain was ignored and undertreated. PUAEME008, the nationwide device typically known as Provide Pain Management, exists to close that space in between concept and the bedside. When taught and used well, it furnishes clinicians and -responders to bring alleviation rapidly, securely, and consistently.
This is not nearly pressing analgesics. It is about structured evaluation under pressure, selecting the ideal technique for the patient in front of you, and having the functional discipline to document, turn over, and testimonial. If you are checking out a pain monitoring training course, whether as part of prehospital training or a hospital-based upskill, comprehending how PUAEME008 plays out in the field assists you pick carefully and exercise with confidence.
What PUAEME008 really covers
On paper, PUAEME008 Provide Pain Monitoring sets efficiency criteria around assessing discomfort, carrying out accepted analgesia, checking reactions, and connecting successfully with obtaining groups. In technique, the device is a scaffold for judgment. It requires you to combine medical pattern recognition with plan proficiency and human communication.
The core consists of: developing a reputable pain history under time pressure; using verified devices such as numerical ranking scales, Wong-Baker faces for youngsters, and behavioral signs for clients that can not self-report; preparing and supplying anesthetics within your scope; and observing, documenting, and escalating when the course deviates from plan. It is typically packed into pain monitoring training courses for paramedics, occasion medics, first -responders in remote industry, and some acute care registered nurses, although the certain pharmacology and tools differ by jurisdiction.
I have actually seen two pupils with identical created ratings do very in a different way when traveling. The one that succeeded asked another question, examined another essential indication, and discussed with the person instead of dealing with the chart. That is the difference PUAEME008 aims to cultivate.
Pain assessment when secs matter
A structured analysis does not imply slow. Done well, it ends up being a pattern you can run while moving down a hallway or packing a client right into a car. Begin by anchoring the essentials: place, start, character, intensity, radiation, organization with activity or breathing, and any type of red flags such as syncope, shortness of breath, or neurological deficits. Too many medical professionals stop after a solitary numerical score. Numbers without context mislead. A "4 out of 10" from a patient farmer with a flail upper body does not equal a "7 out of 10" from a kid with a sprained ankle.
Observe for nonverbal cues. Guarding, pallor, diaphoresis, tachycardia, altered breathing pattern, and agitation fill in gaps when a person can not offer detail. For kids under seven or for nonverbal grownups, behavior scales are commonly a lot more exact than trying to compel a number. PUAEME008 emphasises these selections, and a great discomfort management training course will certainly pierce them till they are 2nd nature.
Reassessment is where many beginners slip. Pain seldom holds still. Activity, splinting, oxygen, and even peace of mind can move it. Recheck after treatments at periods established by your procedure, frequently every 5 to 10 mins originally, then much less frequently once steady. Record not only the score, but the individual's language. "Feels much less sharp, a lot more pressure." Those words matter, particularly when handing over.
Pharmacology within scope: alternatives and trade-offs
Protocols establish what you can give. Within PUAEME008 provide pain monitoring structures, the common suspects include breathed in methoxyflurane, fentanyl (intranasal or intravenous), morphine, ketamine in sub-dissociative doses, nitrous oxide 50-50 blends, and dental agents where time and GI condition allow. Each has sweet places and pitfalls.
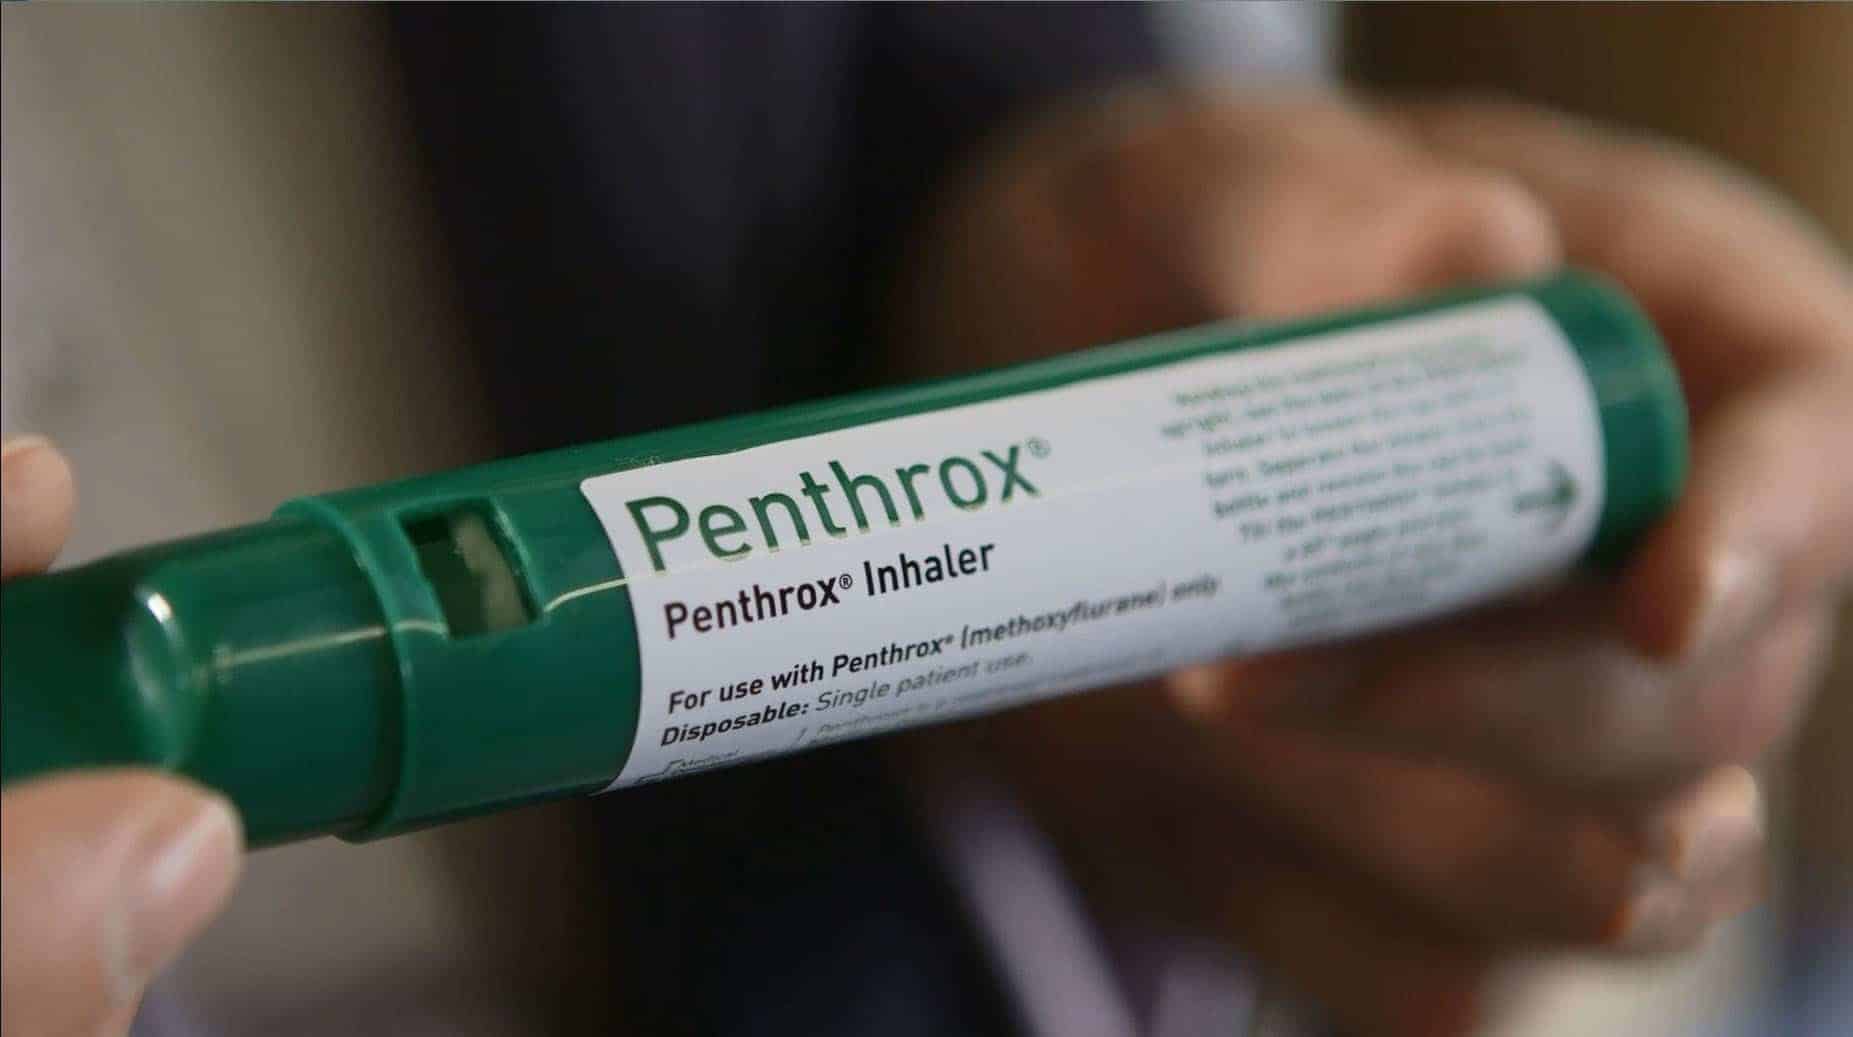
Methoxyflurane purchases time. It is rapid to deliver, portable, and well tolerated. I have used it on a hill while awaiting a stretcher, its familiar apple-pear scent a small comfort on a bad day. It is superb for moderate stressful pain when IV gain access to is postponed or otherwise required. It is much less suitable for patients with considerable respiratory system compromise or prolonged management needs.
Intranasal fentanyl is a workhorse for quick analgesia without IV. It shines in pediatric fractures and adult arm or leg injuries, with a clean pharmacokinetic account and easy titration. Look for breathing depression, especially in older adults or when incorporated with sedatives. Clear interaction with your companion protects against stacking dosages as well fast.
Morphine stays trusted for extreme pain, but it demands careful titration and tracking for hypotension and oversedation. I save IV morphine for people who need continual relief and in setups where continuous monitoring is feasible. It sets well with antiemetics in clients prone to nausea.
Sub-dissociative ketamine has grown in popularity because it protects respiratory tract reflexes while delivering strong analgesia and decreasing opioid requirements. It can generate dysphoria or development sensations, which are disturbing if you have actually not prepared the patient. A quiet explanation and a calm tone lower that threat. Ketamine also assists in people with hypotension where opioids may aggravate hemodynamics.
Nitrous oxide is effective and acquainted in some systems, less readily available in others. It calls for person collaboration and is improperly suited to those with breast injuries or presumed pneumothorax. In the appropriate instance, it offers quick control with very little recurring effects.
Nonpharmacological adjuncts often get hidden under the excitement of drugs, yet they pay rewards. Splint well. Pad pressure factors. Usage cold packs sensibly. Change the setting, dim harsh lights in migraine headache, limit unneeded activity. A well-applied vacuum splint can lower a discomfort rating by 2 factors prior to any type of medicine reaches the bloodstream.
Scope and plan: knowing the edges
PUAEME008 does not approve carte blanche. Your company's medical direction and regional legislation figure out which agents and paths are allowable. The most safe clinicians are those who know their edge instances by heart. Usual plan anchors include minimal age thresholds for methoxyflurane, advancing dose limits for fentanyl and morphine, contraindications for ketamine in particular psychoses or unchecked hypertension, and oxygen needs for nitrous oxide delivery.
When doubtful, call early for scientific consultation if your system permits it. I when managed a young adult with a femoral crack that had actually taken unknown recreational substances. The mix of energizer poisoning and injury made opioid dosing treacherous. A quick seek advice from supported a ketamine-first approach with conventional titration and continual tracking. Good judgment in these tight corners comes from training and from admitting uncertainty when it matters.
Communication as an analgesic
Tone adjustments physiology. Self-respect decreases supportive drive. Easy, straightforward sentences lower anxiety. "You are safe. We are going to manage your discomfort. You will have the ability to breathe." I have actually seen discomfort ratings go down a notch with those words alone.
Trust additionally safeguards versus dosing errors. When an individual believes you are paying attention, they share critical details: last dose of oxycodone, patches on their skin, a history of opioid-induced apnea, or poorly managed rest apnea. For older grownups, verify medicine checklists and inquire about anticoagulants, as bleeding danger can improve your working diagnosis and influence your choice of analgesic and transport priority.
The handover seals care continuity. A useful handover narrates: mechanism of injury or beginning context, baseline discomfort summary, modifications after each intervention, complete doses with timing, vitals patterns, and any kind of negative effects. A rushed recounting of numbers without arc leaves the receiving group reconstructing your reasoning. Strong PUAEME008 training demands that narrative clarity.
Special populaces that evaluate your craft
Pediatrics typically daunts brand-new medical professionals. The antidote is prep work. Use weight-based dosing graphes, keep intranasal tools within reach, and employ caregivers to hold and soothe. Kids mirror grown-up stress and anxiety. If you remain steady, they will certainly typically resolve sufficient to approve splinting and intranasal analgesia without tears. Expect dehydration in extended stomach discomfort, and avoid duplicating invasive efforts that can wait on a regulated environment.
Older grownups offer a different problem. Their pain tolerance differs extensively, and their physiology conceals problem. A small fall with rib fractures can spiral right into hypoventilation and pneumonia if website pain is undertreated. Balance effective analgesia with loss risk and ecstasy avoidance. Low-dose titrated opioids or ketamine, aggressive regional support where readily available, and early participation of receiving groups make a difference.
Pregnancy changes whatever from gastric draining to respiratory system book. Use left lateral tilt when viable, monitor fetal activities if advanced gestation, and choose representatives with well-known security accounts in your system. Nonpharmacologic procedures and regional blocks, if within scope and ability, can save systemic drug exposure.
For patients with compound usage conditions, think a higher standard resistance and a higher threat of respiratory anxiety if sedatives or alcohol are on board. Offer analgesia without judgment, yet prepare for respiratory tract assistance. Entailing allied health early, when possible, improves longer-term outcomes and decreases the rotating door effect.
When the diagnosis hides under the pain
Not every agonizing discussion is a green light for full-dose opioids. Intense abdomen with unclear etiology, serious migraine with neurologic adjustments, or breast discomfort with hemodynamic instability each ask for an intentional rate. The old myth that analgesia covers medical diagnosis has actually been mainly disproved, yet timing and option of agent still matter.
For suspected abdominal catastrophes, moderate, titrated analgesia combined with mindful reassessment preserves examination energy while appreciating the person's distress. In severe migraine with red flags, treat discomfort while relocating quickly toward conclusive imaging and supportive treatment, guarding against oversedation that might cloud neurologic analyses. Upper body discomfort needs integrated analgesia and antiplatelet or anticoagulant treatment per procedure, alongside rhythm monitoring and nitrates if indicated. Great care lives in assimilation, out single-track thinking.
Training that modifications just how you practice
The ideal pain administration programs develop muscular tissue memory under practical restrictions. Manikins and situation scenarios serve, however nothing changes online, unpleasant technique: deciding dosing while the high blood pressure alarm system tweets, training breathing via contractions while a 2nd patient calls your name, or evaluating the dangers of another fentanyl aliquot in a person whose oxygen saturation just dipped.
When picking a pain monitoring certification course, search for programs that combine:
- Scenario-based simulations that call for prioritization, review, and handover under time pressure Pharmacology sessions that teach mechanism, communications, and unfavorable occasion administration, not simply dosing tables
Assessment must be more than a created examination. Expertise demonstrations, medicine preparation drills, negative occasion acknowledgment, and interaction scenarios disclose whether discovering translates to activity. For registered nurses branching into urgent treatment or access environments, discomfort management training courses for registered nurses that integrate PUAEME008 expertises with triage systems and local formularies supply the most effective worth. Physiotherapists working in acute bone and joint setups additionally take advantage of pain administration training courses for physio therapists that emphasize nonpharmacologic techniques along with interdisciplinary sychronisation; if pharmacologic management is out of extent, the training needs to still cover recognition of undertreatment and acceleration pathways.
Short courses hurting management can be rewarding, yet examine that "short" does not suggest shallow. A concentrated one-day program can supply targeted skills, for example, intranasal analgesia in pediatrics or ketamine titration for trauma, offered it consists of monitored technique and post-course mentoring. A certification course suffering monitoring that promises broad capacity should consist of supervised medical time or durable simulation to warrant a pain monitoring certification.
Documentation protects patients and clinicians
No one appreciates paperwork in the heat of method, pain management training courses however a clean record becomes part of the therapy. It tells the next medical professional what functioned and what did not, it secures the person from duplicated application, and it shields you when outcomes are questioned days later.
Elements to videotape include the standard pain description, purpose indicators, the reasoning for agent option, dosage and time, route, client response, vitals fads, damaging occasions and mitigation, and the web content of the handover. If you deviated from a standard series due to a patient-specific element, compose the factor in a complete sentence. That routine constructs count on your medical judgment.

Building a culture of timely analgesia
Individuals can practice well, yet systems still fall short patients if culture punishes analgesia as risky or optional. I have worked in services where pain relief needed three signatures, and the predictable result was enduring. It took a data-driven debate to alter minds: time to first analgesia dropped by 40 percent after protocol simplification, and there was no increase in respiratory system concession when keeping an eye on criteria were kept. The management after that ingrained analgesia metrics into quality control panels, and the culture shifted.
If you are in a placement to influence policy, advocate for simple access to approved agents, standardized lists for preparation and surveillance, and normal instance examines that concentrate on discovering rather than blame. Tie pain metrics to patient experience responses, not as a score to chase after blindly, yet as one essential indicator of caring care.
Practical pointers from the field
Over years of teaching PUAEME008 provide discomfort management, a few small practices maintain paying off.
- Prime your set for the initial ten mins. Keep intranasal atomizers preloaded and identified by dose range, methoxyflurane within reach, and tape pre-cut for splints. The faster you can act, the cleaner your decision-making.
Practice a dose-talk manuscript. People and households kick back when they listen to certain, regular descriptions: call the medication, anticipated benefits, common adverse effects, and what you will certainly do to monitor.
Think in pairs. One medical professional prepares and carries out, the other watches respiratory tract, ventilation, and psychological condition. Also in a tiny team, mark roles clearly for high-risk moments.
Use the discomfort range as a conversation starter, not a decision. Ask what number would allow them move or take a breath even more comfortably, after that go for that target instead of zero.
Plan the next step before you supply the existing one. If this dose does not work, what is your 2nd line, what are the contraindications, and when will you reassess?
Those micro-skills make the difference between certain care and chaotic improvisation.
Where PUAEME008 fits amongst broader certifications
Many clinicians collect badges, and not all badges equate to better care. A discomfort monitoring certificate verifies you have actually satisfied a requirement, however recurring skills originates from deliberate practice. If you are taking into consideration a pain management certification course, straighten it with your workplace. Prehospital medical professionals benefit from programs linked to actual functional medication lists, gadgets, and paperwork systems. Hospital-based team might like components that cover nerve blocks, infusion pumps, and multimodal analgesia pathways.
For registered nurses in immediate care or ED triage duties, pain monitoring training for nurses that mixes pharmacology, trauma evaluation, and communication training boosts both throughput and client contentment. For allied health experts, a pain management certificate training course can clarify borders and rise pathways, protecting against harmful hold-ups when pharmacologic discomfort control is appropriate.
The highest-yield programs close the loop with mentorship. A solitary day of lectures does not alter reflexes. A month of on-shift mentoring does.
Measuring success past the discomfort score
Pain scores relocate the needle, however they are not the only end result worth monitoring. I try to find fewer unscheduled returns due to poor analgesia, much shorter time to mobilization in basic fractures, lower occurrence of oxygen desaturation throughout opioid usage, and much better handover quality. Person remarks inform you more than study numerics. If individuals point out feeling heard, safe, and sustained, your analgesia practice is most likely sound.
Systems that installed PUAEME008 standards see downstream gains in sedation security, decreased anxiety throughout transport, and tighter teamwork. Those gains compound. Much less mayhem implies fewer mistakes, and fewer mistakes suggest more energy for the next individual who requires your finest judgment.
Final ideas from the sharp end
Pain is a professional trouble and an ethical one. When somebody trusts you with their suffering, they are not requesting heroics. They are requesting for focus, ability, and follow-through. PUAEME008 orders that agreement right into proficiencies you can exercise, examination, and refine.

If you are choosing amongst pain management training programs, select the one that requires your presence, not simply your attendance. Ask how they teach emergency situation discomfort monitoring under realistic constraints, how they assess communication, and just how they keep your abilities to life after the certificate is mounted. Whether you are discovering a provide pain monitoring program as your first step or adding a discomfort monitoring accreditation to an established occupation, deal with the unit as the start of a habit: examine with curiosity, treat with accuracy, and circle back to see if you genuinely helped.
The days that stick with me are not the huge conserves. They are the peaceful success, like the distressed child that was laughing by the time we reached radiology because somebody took five extra minutes to describe the intranasal spray and hold a hand. That is the conventional worth training for, and the assurance behind any type of course that claims to show pain well.